An eight-year-old boy came into my ER with a month-old cast and a dangerously high fever, but his mother insisted it was only a mild flu. When I told her the cast had to come off immediately, she suddenly begged me not to open it. I thought she was simply afraid of what we might find—until she admitted her son had been trying to tell her something was wrong for days.
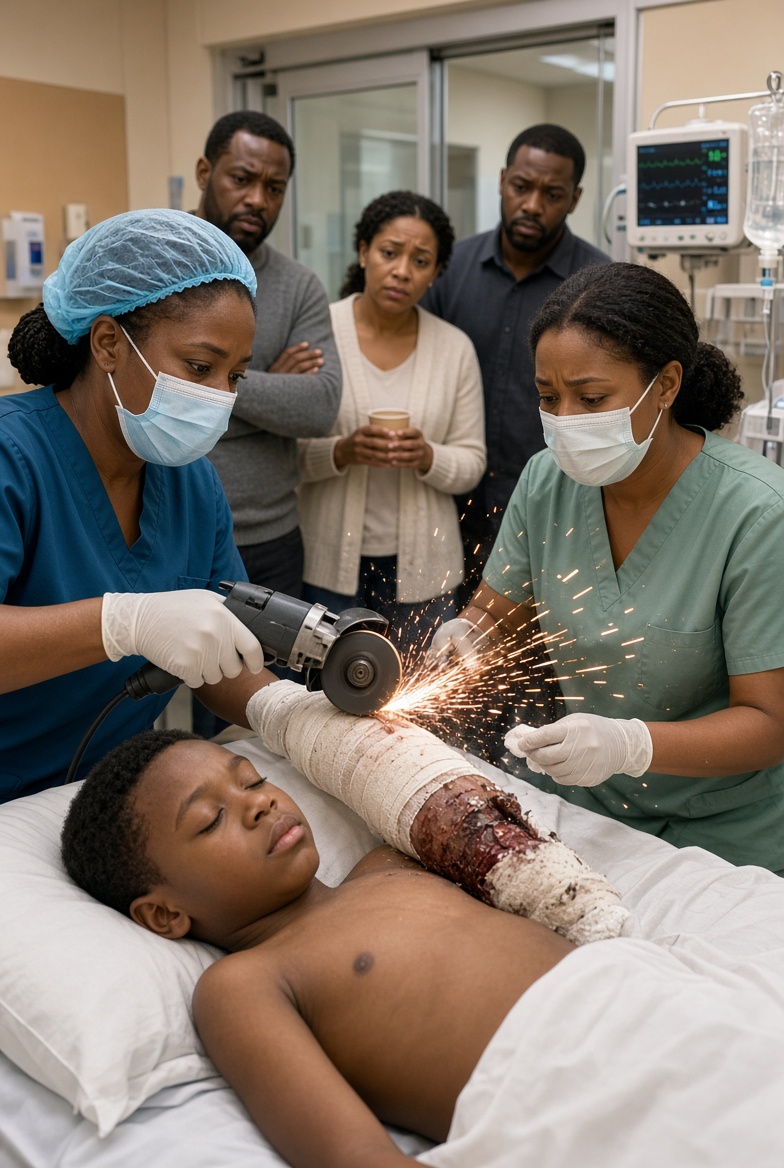
An Eight-Year-Old Boy Was Brought Into My ER With a Cast That Had Been On for Nearly a Month and a Fever High Enough to Alarm Me
The odor reached us before the stretcher even rolled through the emergency-room entrance. It was sickly sweet, metallic, and unmistakably rotten, strong enough to cut through the normal smell of disinfectant and sterile hospital air and make everyone near the nurses' station realize this was not going to be an ordinary case. My name is Dr. Naomi Ellery, and after eight years working in emergency medicine, I had learned that some of the most disturbing cases arrived without chaos. There were no screaming relatives, no dramatic explanations, and sometimes no obvious injuries—just a dangerously sick child standing beside an adult who kept insisting that nothing serious was happening. Desmond, one of our nurses, rushed toward me with his hand pressed over his mask. His face was pale as he told me an eight-year-old boy had just been brought in with a fever of 103.8, a heart rate close to 140, dropping blood pressure, and such severe lethargy that he could barely respond when staff spoke to him. "His mother says it's just the flu." Desmond glanced toward Trauma Room 2. "But you need to look at his arm." The second I opened the sliding door, the smell became almost unbearable. The boy on the stretcher looked smaller than eight, with cracked lips, sunken cheeks, and waxy pale skin that suggested his body had been fighting something serious for far longer than a few hours. His right arm lay stiffly at his side inside a fiberglass cast that ran from his knuckles to above his elbow. The cast was filthy, covered in layers of dark staining, and the material around his hand had tightened against badly swollen skin. His exposed fingers were purple, and the tips had already begun turning blue. I pressed gently against one fingertip and watched carefully. The color did not return. "How long has he been wearing this cast?" His mother stood near the corner holding a Starbucks cup as casually as if she were waiting for a routine checkup. Diane Whitcombe wore a cream-colored sweater, pearls, perfectly manicured nails, and a polished blonde bob, looking strangely untouched by the emergency unfolding only a few feet away. "Oh, around a month," she said with a shrug. "He's clumsy. He's always falling out of trees in the backyard." She took another sip of her coffee. "We only brought him in because he felt warm this morning. It's probably some seasonal virus." Nothing about the child in front of me looked remotely like a mild viral illness. His vital signs were consistent with septic shock, and the discoloration in his fingers told me the swelling beneath the cast was already interfering with blood flow. "Mrs. Whitcombe, your son is critically ill," I told her. "That cast has to be removed immediately." I kept my voice calm, but I made sure she understood the seriousness. "He could lose his hand. And if the infection has spread as far as I suspect, his life could be in danger." I expected panic, fear, or at least disbelief. Instead, irritation flashed across Diane's face as she insisted that his orthopedic surgeon had told her the cast needed to stay on for another two weeks. "No," she said firmly. "Just give him antibiotics and we'll go home." Wanda, one of our most experienced nurses, had already pulled on a second mask and rubbed peppermint oil beneath her nose because the odor from the cast was so intense. Even her hands were slightly unsteady as she fastened the blood-pressure cuff around the boy while Desmond prepared pediatric IV access and activated our sepsis protocol. I had seen neglected children before, and I had learned that neglect did not always arrive looking dirty or chaotic. Sometimes it walked into a hospital wearing expensive clothes, carrying a premium coffee, and speaking so calmly that people were tempted to believe explanations that completely contradicted what they could see with their own eyes. Three years earlier, I had allowed myself to be reassured too easily. A caregiver had offered polished, convincing explanations for injuries that did not quite make sense. I documented my concerns and asked questions, but I stopped pushing when the answers sounded reasonable enough. The child returned to the hospital later in far worse condition, and I had carried that memory into every pediatric case since. I was not going to make the same mistake again. "Wanda, call security," I said. Then I turned toward the supply cabinet. "And bring me the cast saw." Diane reacted instantly. She rushed toward the stretcher. "You cannot touch him!" "I'll sue this hospital!" Wanda stepped between Diane and her son before she could reach the bed. Two security officers arrived moments later and pulled her farther away, and she fought against them hard enough to wrinkle the immaculate sweater she had walked in wearing. Then Wanda placed the cast saw beside the boy's arm. Everything about Diane changed. The anger disappeared from her face. "Don't open it," she whispered. I turned toward her. "Why?" Her eyes never left the cast. "Please," she said quietly.
Part One: What She Was Hiding
I looked at her for a long moment, security still holding her a careful distance from the stretcher, the boy's ragged breathing the only sound cutting through the tension. "Mrs. Whitcombe," I said, keeping my voice level, "your son's life is at risk right now. I need you to tell me exactly what you're afraid I'm going to find." Her composure, so carefully maintained since the moment she'd walked through our doors, finally began to crumble. "He kept telling me something felt wrong," she said, her voice barely above a whisper. "For days. He said it felt like something was moving inside, that it hurt worse than before. I told him he was imagining it." "Why didn't you bring him in sooner?" Diane's eyes dropped to the floor. "Dr. Prescott said the cast couldn't come off early," she said. "He said interrupting the healing process could set back the fracture by weeks. I didn't want to be the mother who ignored medical advice." Something about the way she said it, rehearsed, almost performative, made the hair on my arms rise. "What fracture, exactly?" I asked. "What happened to break his arm in the first place?" "He fell," she said. "From the treehouse in our backyard. Six weeks ago." I glanced at the boy's chart, hastily started by triage, the single line under "reported injury history" reading simply: multiple prior fractures, same arm, past eighteen months. "This isn't his first fracture in that arm," I said. Diane's silence answered the question more clearly than any explanation could have.
Part Two: Opening the Cast
I made the decision without waiting for further permission, security keeping Diane at a controlled distance as Wanda activated the oscillating saw, its low hum filling the trauma room as she carefully worked along the seam of the cast. The smell, already overwhelming, intensified the moment the saw breached the fiberglass shell, a wave of putrid, decayed tissue odor rolling through the room strong enough to make even Desmond, a nurse with fifteen years of emergency experience, step back momentarily to steady himself. Beneath the cast, the boy's arm told a story more horrifying than anything Diane's careful excuses had prepared us for. The skin along his forearm had turned a mottled black and green in several patches, clear signs of necrotizing tissue, while the swelling beneath had grown so severe that the cast itself had begun cutting into what remained of healthy skin, creating deep, infected pressure wounds along nearly the entire length of his arm. "Get ortho and infectious disease down here immediately," I said, my voice sharp with the particular urgency reserved for moments when minutes genuinely mattered. "And prep for possible emergency debridement. This is advanced osteomyelitis, possibly with early necrotizing fasciitis. We need surgery within the hour or he could lose the arm entirely." Wanda worked quickly, cleaning what she could while we waited for the surgical team, though the boy, whose chart now listed his name as Theo Whitcombe, remained barely conscious throughout, his small body simply too depleted by days, possibly weeks, of untreated infection to respond to much beyond the IV fluids and antibiotics already running into his other arm.
Part Three: Dr. Prescott
While the surgical team prepared Theo for emergency debridement, I pulled his full medical history, cross-referencing the "orthopedic surgeon" Diane had repeatedly cited as the authority behind keeping the cast on far longer than any standard fracture would require. Dr. Reginald Prescott, it turned out, held an active medical license but had faced two prior malpractice complaints, both related to unusually extended casting periods for pediatric patients, complaints that had been settled quietly without any formal disciplinary action attached to his record. A call to his office, placed by our hospital's social work department while I continued treating Theo, revealed something even more concerning. Dr. Prescott's own scheduling records showed no appointment for Theo in over five weeks, directly contradicting Diane's claim that he'd personally advised against removing the cast just days earlier. "She's been telling us he approved every decision," the social worker, Naomi Calloway, told me quietly outside Theo's room. "But according to his office, they haven't seen this child since the initial casting. Whatever medical advice she's been citing, it isn't coming from an actual doctor currently treating him." I felt something cold settle in my chest, the particular horror of realizing a parent had been constructing an elaborate, convincing fiction, layer by layer, specifically designed to keep hospital staff and social workers from questioning what was actually happening to her son.
Part Four: The Pattern Emerges
Naomi Calloway, working alongside hospital security and the county's child protective services division, began digging deeper into Theo's medical history, uncovering a pattern that stretched back well beyond the six weeks Diane had claimed for this particular fracture. Records from three different hospitals across two counties showed Theo had been treated for seven separate fractures over the previous eighteen months, each one attributed to some version of ordinary childhood clumsiness: falling from a treehouse, tumbling down stairs, a bicycle accident, a fall from playground equipment. Individually, each incident might have seemed plausible. Collectively, the pattern painted a picture that made Naomi's expression grow increasingly grim as she laid the timeline out for me during a case review. "Seven fractures in eighteen months, all documented at different facilities, none of them cross-referencing each other until now," she said. "That's not accidental. That's someone deliberately spreading these incidents across different hospitals specifically to avoid the kind of pattern recognition that would normally trigger a mandatory abuse investigation." "Munchausen by proxy," I said, the clinical term for the specific, calculated cruelty I was beginning to suspect settling heavily in the room. "Possibly," Naomi said carefully. "Or something adjacent to it. We've also found something else. An active fundraising campaign, running for the past year, describing Theo as suffering from a rare, chronic bone condition requiring ongoing specialized treatment. It's raised just over $94,000."
Part Five: The Fundraiser
Naomi pulled up the campaign on her tablet, a polished, professionally written page hosted on a popular crowdfunding platform, featuring photographs of Theo in various casts and slings over the past year, alongside a detailed, emotionally compelling narrative describing his supposed battle with a rare congenital bone fragility disorder. The medical details, upon closer examination by our hospital's own pediatric orthopedic specialist, Dr. Farrah Okonkwo, didn't hold up to scrutiny. "There's no such diagnosis in his actual medical records," Dr. Okonkwo said, reviewing the campaign alongside Theo's genuine chart. "No genetic testing results, no specialist referrals consistent with what she's describing here. This appears to be an entirely fabricated diagnosis, constructed specifically to support ongoing fundraising." The campaign's donation history showed steady contributions from hundreds of individual donors, many leaving supportive comments referencing updates Diane had posted regularly, describing fictional medical crises, fictional specialist consultations, an entire elaborate narrative sustained through consistent, convincing documentation that had apparently fooled not just hundreds of sympathetic strangers, but multiple hospital systems as well. "She's been injuring him herself," I said, the full weight of the conclusion settling over the room. "Repeatedly. To sustain this narrative." "That's what we need to determine conclusively," Naomi said. "But given everything we're seeing, that's exactly the direction this investigation needs to move."
Part Six: Theo's Surgery
Theo's emergency debridement surgery lasted just under three hours, the surgical team successfully removing the necrotic tissue while preserving enough of his arm's structure and function to avoid amputation, though Dr. Okonkwo cautioned that his long-term recovery would likely involve significant physical therapy and possible additional reconstructive procedures. "We caught it just in time," she told me afterward, both of us still in scrubs outside the recovery room. "Another day, possibly less, and we would have been having a very different conversation about his arm, and possibly about his survival given how advanced the sepsis had become." I sat with Theo during his early recovery, watching him slowly regain consciousness, his eyes fluttering open with the particular confusion of a child waking up in an unfamiliar place, tubes and monitors surrounding him in ways that clearly frightened him before he fully understood where he was. "You're safe," I told him gently. "You're at the hospital. Your arm is going to be okay." Theo's eyes filled with tears, though he didn't cry outright, something in his careful, controlled reaction suggesting a child who'd learned, somewhere along the way, that displaying too much distress carried its own consequences. "Is my mom mad?" he asked quietly. The question broke my heart more than almost anything else that difficult day had contained. "You don't need to worry about that right now," I said. "Right now, we just need you to rest and get better."
Part Seven: The Interview
Once Theo was stable enough for a careful, trauma-informed interview, a specially trained child forensic interviewer named Priya Osei worked with him over several sessions, gently building enough trust and comfort for him to share his own account of what had actually been happening. "Sometimes Mommy says my arm needs to stay hurt a little longer," Theo told Priya during one session, recorded through the specialized one-way observation system designed to minimize additional trauma to child witnesses. "She says the doctors and the people online need to see I'm still sick." "Does your arm hurt on purpose sometimes?" Priya asked gently. "Does something happen to make it hurt more?" Theo hesitated for a long moment before answering. "Sometimes she twists it," he said quietly. "Under the cast. When nobody else is around. She says it's to check if it's healing right, but it always hurts really bad after, and then it feels different for a few days. Worse." Priya kept her expression carefully neutral, though I watched from the observation room as her hands tightened slightly around her notepad. "Thank you for telling me that, Theo," she said. "That was very brave. None of this is your fault." "She said if I ever told anyone, the doctors would take away the money we need for my treatment," Theo said. "And then we wouldn't be able to pay for anything, and it would be my fault."
Part Eight: The Arrest
With Theo's forensic interview, the fabricated medical fundraising campaign, and the pattern of fractures across multiple hospitals all documented and cross-referenced, Naomi Calloway and county detectives moved forward with formal charges against Diane Whitcombe: multiple counts of felony child abuse, medical child abuse specifically related to the pattern of induced injury, and wire fraud connected to the fraudulent crowdfunding campaign. Diane was arrested at her home two days after Theo's surgery, detectives executing a search warrant that recovered additional evidence, including a detailed private journal documenting her manipulation of the fundraising narrative, notes about which symptoms generated the strongest donor response, and records of the specific techniques she'd used to reinjure Theo's arm in ways designed to look consistent with ordinary healing complications rather than deliberate harm. "This is one of the more calculated cases of medical child abuse I've encountered in my career," Detective Odalys Ferreira told me during a case briefing several weeks later. "Most cases we see involve impulsive, poorly planned deception. This involved sustained, methodical planning across multiple institutions, specifically designed to avoid detection for as long as possible." The investigation also revealed that Theo's father, Marcus Whitcombe, had been effectively cut off from his son's medical care following the couple's divorce three years earlier, Diane having used a combination of manipulative custody arrangements and the elaborate medical narrative to justify limiting his access, much the same way she'd used medical explanations to control every other aspect of the situation.
Part Nine: Marcus Whitcombe
Marcus, once notified of the full scope of what had been happening to his son, arrived at the hospital within hours, visibly shaken as Naomi walked him through the documented pattern of abuse that had unfolded largely outside his awareness during the years of limited custody access. "She always had an explanation for why I couldn't see him during his 'treatments,'" Marcus told me, sitting beside Theo's hospital bed once medical staff cleared a supervised visit. "I believed her because why would anyone lie about something like that? Why would anyone fabricate their own child being sick?" "Some people do, for reasons that are difficult for most of us to fully understand," I said. "The important thing now is what happens moving forward." Theo, still recovering, watched his father with a cautious, uncertain hope, the kind of expression that suggested a child slowly relearning what safety might actually look like after years of a distorted, manipulated version of care. "Dad?" Theo said quietly. "Are you going to leave again?" Marcus's composure broke entirely at that question, tears falling freely as he took his son's uninjured hand. "No," he said. "I'm not leaving. Not ever again. I promise you that."
Part Ten: The Custody Case
With criminal charges against Diane moving forward and clear documentation of the medical abuse now part of the official record, Marcus's attorney filed for immediate emergency custody, a request the family court granted without significant hesitation given the overwhelming evidence. Naomi Calloway continued working closely with the family throughout the transition, coordinating Theo's ongoing medical care, physical therapy, and referral to a specialized trauma therapist experienced specifically with cases of medical child abuse, a form of trauma that carried its own particular complexities given how thoroughly Theo's understanding of care, love, and medical treatment had been distorted by his mother's manipulation. "Recovery from this kind of abuse often takes longer than physical recovery from the injuries themselves," Dr. Okonkwo explained during a family care conference. "Theo has spent years learning that pain and sickness were things that earned him attention and care, deliberately engineered by the one person who was supposed to protect him from exactly that kind of harm. Untangling that association is delicate, important work." Marcus committed fully to that process, relocating to be closer to Theo's ongoing medical team, attending every therapy session, slowly rebuilding a relationship with his son that had been systematically undermined for years without his full awareness of exactly why.
Part Eleven: Diane's Trial
Diane's trial, held nearly a year after that first terrible afternoon in Trauma Room 2, drew significant public attention once local media picked up details of the case, the fabricated fundraising campaign proving particularly damning once prosecutors presented the full financial trail alongside Theo's own forensic interview testimony, submitted through the same protective closed-circuit process used in similarly sensitive child abuse cases. The defense attempted to argue that Diane suffered from a genuine, if misguided, psychological compulsion rather than calculated criminal intent, presenting expert testimony regarding factitious disorder imposed on another, the clinical diagnosis most closely associated with the pattern of behavior investigators had documented. The prosecution countered effectively by highlighting the financial fraud component, arguing that regardless of any underlying psychological factors, Diane's detailed journal entries tracking donor response to specific fabricated symptoms demonstrated clear awareness that her actions were deceptive, calculated, and financially motivated rather than purely compulsive. The jury ultimately convicted Diane on all major counts, the judge, during sentencing, specifically noting the calculated, sustained nature of the abuse as an aggravating factor, sentencing her to eighteen years in prison alongside a restitution order requiring repayment of the fraudulently obtained fundraising money, funds that were redirected, once recovered, into a trust established for Theo's ongoing medical and therapeutic care.
Part Twelve: Theo's Recovery
Theo's physical recovery continued steadily over the following year, his arm regaining significant function through consistent physical therapy, though Dr. Okonkwo noted he would likely always carry some reduced grip strength and visible scarring from both the original injuries and the emergency surgery that had ultimately saved the limb. His emotional recovery followed a slower, more complicated path, his trauma therapist, Dr. Ines Calloway, working patiently with him to help rebuild a healthy understanding of what genuine care and safety actually looked like, separate from the distorted version his mother had constructed around manufactured illness and injury. Marcus adjusted his entire life around supporting that recovery, taking a position with more flexible hours, ensuring he was present for every appointment, every difficult evening, every small, hard-won milestone along Theo's path back toward something resembling ordinary childhood. "He asked me last week if it was okay to just be a normal kid," Marcus told me during a follow-up visit nearly eighteen months after Theo's initial admission. "If he was allowed to just play outside and get regular scrapes without it needing to mean something bigger. I don't think I've ever felt my heart break and heal at exactly the same moment before."
Part Thirteen: Changes in Practice
Theo's case, once it became part of medical literature discussions regarding medical child abuse detection, prompted significant changes in how our hospital system approached cases involving prolonged casting periods, cross-referencing patient histories across regional hospital networks specifically to catch the kind of pattern that had allowed Diane's abuse to continue undetected for so long. I worked with our hospital's pediatric safety committee to help develop new protocols, mandatory verification of cited treating physicians for any case involving parental refusal of standard medical intervention, and improved information sharing between regional facilities specifically designed to surface exactly the kind of pattern that had taken months to fully piece together in Theo's case. "Cases like this are rare," I told a room of new emergency medicine residents during a training session built around what we'd learned. "But when they happen, they're catastrophic if missed. The lesson isn't to distrust every parent who seems calm or well-dressed or medically informed. The lesson is to trust the physical evidence in front of you, every single time, regardless of how convincing the explanation sounds."
Part Fourteen: Two Years Later
Two years after that first overwhelming smell rolled through our emergency room doors, I received a card in the mail, addressed in careful, still slightly uneven handwriting, from Theo Whitcombe. Inside, alongside a crayon drawing of what appeared to be a treehouse, considerably less dramatic than the one that had once served as his mother's cover story, he'd written a simple message: Thank you for not believing her. I'm doing okay now. I kept that card pinned above my desk in the physician's lounge, a quiet, powerful reminder of exactly why the instinct to keep asking questions, even when answers sounded reasonable, even when a parent's composure suggested nothing could possibly be wrong, remained one of the most important tools available in emergency medicine. Marcus sent occasional updates as well, photographs of Theo at physical therapy milestones, a school art show where one of his paintings had won a small ribbon, ordinary, unremarkable moments that carried extraordinary weight given everything it had taken to reach them. I thought often about that afternoon, Diane's composed, irritated insistence that nothing was wrong, the cast saw's hum cutting through the tension, the moment her careful mask finally slipped and revealed, however briefly, the fear beneath everything she'd constructed. Please, she'd whispered. Don't open it. I had opened it anyway, and in doing so, had given an eight-year-old boy the chance to finally, actually heal.
The End.
My Mother Wore Her Oldest Dress to My Engagement Dinner—Then She Told Me the Real Person She Was Testing

PART 2
“My dress wasn’t really for his parents,” Mom whispered.
“It was for Ethan.”
I stared at her reflection in the mirror.
Ethan was my fiancé.
The man I planned to marry in four months.
“What do you mean?”
Mom turned away from the sink.
“His parents can be snobs. That would be unpleasant, but you aren’t
marrying them.”
She paused.
“You’re marrying him.”
I felt my stomach tighten.
“What exactly were you watching?”
“Whether he would protect someone when protecting them might embarrass
him.”
I started to answer, then stopped.
Mom continued quietly.
“I wanted to know whether Ethan would notice what his mother was doing.
Whether he would laugh. Whether he would stay silent because correcting
her would be uncomfortable. Whether he would join in because he wanted
her approval.”
Every moment of dinner replayed in my head.
Ethan had not laughed.
But he had not said much either.
When his mother made the comment about Mom’s dress, his jaw tightened.
When she asked whether Mom had ever eaten somewhere like this, Ethan
immediately changed the subject.
At the time, I had been grateful.
Now Mom shook her head.
“Changing the subject is not the same as standing up for someone.”
That sentence landed hard.
“Do you think he failed?”
“I think dessert hasn’t arrived yet.”
PART 3
I stared at her.
“You planned something else?”
Mom smiled.
“No.”
“Then why does dessert matter?”
“Because his mother has been building toward something all evening.”
I frowned.
“How do you know?”
“Because I spent twenty-five years working customer service, sweetheart.
People who want to humiliate you rarely stop when they’re enjoying
themselves.”
That was my mother.
She had worked as a grocery cashier in the mornings and cleaned offices
at night when I was young.
She could read a room faster than anyone I knew.
I suddenly felt ashamed for assuming the old dress meant she did not
understand the room.
She understood it better than I did.
“Come on,” she said.
We returned to the table.
Ethan looked up immediately.
“You okay?”
“Yes.”
His eyes moved toward my mother.
“Mrs. Carter?”
Mom smiled.
“Perfectly fine.”
His mother, Victoria Whitmore, lifted her wineglass.
“Wonderful. We were just discussing the wedding.”
Something in Mom’s expression told me she had been right.
Dessert had not arrived.
But the next test already had.
PART 4
Victoria unfolded a cream-colored folder beside her plate.
“I hope you don’t mind,” she said, “but I took the liberty of making a
few notes.”
Ethan sighed.
“Mom.”
“What? Someone has to think practically.”
She opened the folder.
Inside were pages of wedding estimates.
Venue.
Flowers.
Catering.
Photography.
Transportation.
The numbers made my head spin.
Victoria tapped one page.
“Obviously, we’re happy to cover the reception.”
My father-in-law-to-be, Robert, nodded.
“But,” Victoria continued, “there are traditions.”
Her eyes moved toward my mother.
“The bride’s family generally contributes too.”
Mom smiled.
“Of course.”
Victoria tilted her head.
“I don’t want anyone to feel pressured.”
The sentence sounded considerate.
It was not.
She slid a paper across the table.
“There are smaller items. Invitations. Bridesmaid gifts. Perhaps the
rehearsal dinner, although even that may be a little ambitious.”
My cheeks burned.
“Victoria, Mom doesn’t need to—”
Mom touched my wrist.
“It’s okay.”
Victoria smiled.
“We simply want everyone to participate at a level that makes sense for
them.”
Then she added:
“Even something symbolic would be appreciated.”
That was when Ethan put down his fork.
PART 5
“Mom, stop.”
Victoria blinked.
“I’m discussing the wedding.”
“No. You’re discussing Claire’s mother’s finances.”
My heart slammed against my ribs.
Victoria’s smile disappeared.
“I am doing nothing of the sort.”
“You’ve been doing it all evening.”
Robert looked at his son.
“Ethan.”
But Ethan continued.
“You commented on her clothes before she sat down.”
“I complimented her.”
“You asked whether she had ever eaten in a restaurant like this.”
“It was conversation.”
“You mentioned the wine price three times.”
Victoria stared at him.
“I didn’t realize I was being audited.”
“You aren’t.”
Ethan’s voice remained calm.
“But I’m not going to sit here while you make Mrs. Carter prove she
belongs at our table.”
Nobody spoke.
Mom looked at me.
Not triumphantly.
Just carefully.
This was what she had been waiting for.
Ethan had finally stopped changing the subject.
He had named the behavior.
PART 6
Victoria’s face hardened.
“You’re embarrassing me.”
Ethan nodded once.
“I know.”
The simplicity of his answer stunned her.
Robert cleared his throat.
“Maybe everyone is reading too much into this.”
Mom finally spoke.
“I don’t think so.”
Victoria turned toward her.
Mom folded her napkin neatly.
“I wore this dress deliberately.”
I closed my eyes for half a second.
Here we go.
Victoria looked confused.
Mom continued.
“My daughter knows I own better clothes.”
Victoria’s gaze moved toward me.
“I wanted to see how people at this table would treat me if they
believed I had very little money and no social value to them.”
Robert’s eyebrows rose.
Victoria’s face went pale, then red.
“You tested us?”
“Yes.”
“How manipulative.”
Mom nodded.
“Possibly.”
I had not expected her to admit it.
She continued.
“It was not my finest idea. But I have one daughter, and she is marrying
into a family with far more money than ours. I needed to understand
whether money would become a weapon.”
Victoria pushed back slightly from the table.
“And you think one dress tells you that?”
“No.”
Mom looked at Ethan.
“People do.”
PART 7
Ethan looked uncomfortable.
Not angry.
Uncomfortable.
That mattered.
Mom turned to him.
“You were quiet too long.”
He nodded.
“I know.”
“You tried to redirect your mother instead of confronting her.”
“I know.”
“Why?”
Ethan looked at Victoria.
“Because this is what I’ve always done.”
Victoria stiffened.
He continued.
“When Mom gets like this, Dad changes the subject. I change the subject.
Everyone lets it pass because confronting her makes dinner worse.”
Robert looked down.
Victoria said, “Gets like what?”
Ethan met her eyes.
“Classist.”
The word seemed to freeze the table.
Victoria’s mouth opened.
Then closed.
I expected shouting.
Instead, she whispered, “That is a horrible thing to call your mother.”
Ethan shook his head.
“I’m not calling you a horrible person. I’m describing what you did
tonight.”
Mom glanced at me again.
The test was no longer about whether Ethan would defend her.
It was about whether he could tell the truth after realizing he had
waited too long.
PART 8
Dessert arrived at the worst possible moment.
Our server, Daniel, approached carrying five plates of chocolate mousse.
He took one look at the table and slowed down.
“Should I come back?”
Mom smiled.
“No, young man. Chocolate may be the only thing capable of saving us.”
Daniel placed the desserts down and escaped.
For a few seconds, everyone stared at chocolate.
Then Robert laughed.
Not loudly.
But genuinely.
Victoria glared at him.
“I’m sorry,” he said. “That was funny.”
Even I smiled.
The tension cracked just enough for us to breathe.
Then Mom said something I did not expect.
“Victoria, I owe you an apology too.”
Victoria looked suspicious.
“For what?”
“For setting a trap instead of simply coming to dinner as myself.”
I turned toward Mom.
She continued.
“I wanted information. I got it. But tests can become their own kind of
dishonesty.”
Victoria stared at her.
Mom touched the faded sleeve.
“This dress belonged to my sister.”
I had not known that.
“She died when Claire was little. I kept it because I couldn’t throw it
away.”
Suddenly the dress meant something entirely different.
PART 9
Mom had not chosen random shabby clothing.
She had chosen something precious that looked worthless to strangers.
“My sister bought this dress for twenty-eight dollars,” Mom said. “She
wore it to every important event she could because twenty-eight dollars
was a lot for her then.”
Victoria looked at the faded flowers.
“She would have thought this restaurant was ridiculous.”
Robert smiled.
“I’m beginning to like your sister.”
“She would have liked you.”
Mom looked at Victoria.
“My point is not that expensive things are bad. My daughter likes
beautiful things. So do I.”
She gestured around the restaurant.
“My point is that price is not a reliable measure of value.”
Victoria’s expression shifted.
For the first time all evening, she seemed less defensive than
embarrassed.
She looked at me.
“Claire, did I make you feel that your mother was not good enough for
us?”
I hesitated.
“Yes.”
That answer hurt her.
I could see it.
But I was done smoothing the edges.
PART 10
Victoria looked down at her dessert.
“I grew up poor.”
Nobody expected that.
Not even Ethan.
“What?” he asked.
She gave a short laugh.
“You think your grandfather always had money?”
Ethan frowned.
Victoria explained that her father had been a postal worker and her
mother a school cafeteria employee.
Their family lived in a two-bedroom apartment until Victoria was
seventeen.
She earned scholarships.
Later, she married Robert when his family business was still small.
The wealth came gradually.
“So why…” I began.
Victoria answered before I finished.
“Because I spent years being terrified people would know.”
Mom understood immediately.
“You learned to identify the things people used to judge you.”
Victoria nodded.
“Clothes. Restaurants. Table manners. Wine. Neighborhoods.”
“And then you started using the same measurements.”
Victoria’s eyes filled.
“Yes.”
The admission did not erase the evening.
But it changed its direction.
PART 11
Robert finally spoke.
“I should have stopped it too.”
Victoria looked at him.
He shrugged sadly.
“Ethan was right. I redirect you.”
“For thirty-two years?”
“Approximately.”
She almost smiled.
Then Robert looked at Mom.
“I’m sorry.”
Mom nodded.
“Thank you.”
Ethan turned toward me.
“I owe you an apology.”
“You defended Mom.”
“Eventually.”
He did not let himself escape through the good thing he had finally
done.
“I saw what was happening earlier. I wanted Mom to stop without making
her angry.”
“That’s true.”
“I was protecting the dinner.”
He paused.
“Not you.”
That was exactly what Mom had been testing.
Could Ethan recognize the difference between keeping peace and
protecting people?
I reached for his hand.
“I don’t need you to fight your parents every time they annoy me.”
“I know.”
“But if someone is humiliating me or my mother…”
“I need to say it.”
“Yes.”
He squeezed my fingers.
“I will.”
Mom immediately interrupted.
“Careful with promises.”
PART 12
We all looked at her.
She pointed her spoon at Ethan.
“Don’t promise perfection. Promise you’ll notice sooner.”
Ethan smiled.
“I can promise that.”
Victoria sighed.
“Am I allowed to promise anything?”
Mom considered.
“You can promise never to ask me whether I’ve eaten in a fancy
restaurant again.”
Robert laughed.
Victoria covered her face.
“I deserve that.”
The rest of dinner was awkward.
But it was honest.
We discussed the wedding budget again.
This time, I told Victoria clearly that Mom would not be assigned
expenses to demonstrate participation.
Mom could contribute whatever she wanted.
Or nothing.
Victoria agreed.
Then Mom surprised everyone.
“I’ll pay for the flowers.”
I stared at her.
“Mom.”
“What?”
“Flowers are expensive.”
“I know.”
Victoria looked confused.
Mom smiled.
“I didn’t say I was broke.”
That sentence nearly made Ethan choke on his water.
PART 13
After dinner, Mom and I walked to the parking garage together.
I turned on her.
“How much money do you have?”
She laughed.
“Enough.”
“Mom.”
“I worked two jobs for years, Claire. I also saved. Then I bought a tiny
house before your neighborhood became fashionable.”
I stared.
She had sold that house three years earlier and moved into a smaller
condo.
I had assumed the sale simply funded retirement.
Apparently, she had done better than I knew.
“I’m not rich like the Whitmores,” she said. “But I’m comfortable.”
“So the entire poor-mother act…”
“I never said I was poor.”
“You wore Aunt Lisa’s ancient dress.”
“Because I love it.”
“You let Victoria think—”
Mom stopped walking.
“No.”
Her expression became serious.
“She decided.”
That distinction stayed with me.
Mom had not lied about her job, education, home, or finances.
She simply wore an inexpensive old dress.
Everything else had been supplied by assumption.
PART 14
On the drive home, Ethan was quiet.
Finally he said, “Your mother scares me.”
“She should.”
“She planned that whole thing.”
“Yes.”
“Does she test everyone?”
“No.”
“That answer was too fast.”
I laughed.
Then he became serious.
“Are you reconsidering us?”
I looked out the window.
“I’m reconsidering what marriage means when two families have different
relationships with money.”
“That sounds ominous.”
“It’s practical.”
We talked for almost two hours after reaching my apartment.
Not about the restaurant.
About us.
Our salaries.
Debt.
Savings.
Future children.
Whether we expected to support parents financially.
Whether gifts from his family would come with influence.
Whether I felt pressure to maintain their lifestyle.
Whether Ethan expected me to leave work after children.
We had discussed some of those things before.
Never this directly.
Mom’s ridiculous dress had opened a conversation our engagement ring had
somehow avoided.
PART 15
The biggest surprise came when Ethan admitted he had a trust fund.
I knew his family was wealthy.
I did not know the amount.
He looked embarrassed.
“Why didn’t you tell me?”
“I didn’t want money to affect how you saw me.”
I stared at him.
Then I laughed.
“What?”
“You and my mother are more alike than either of you wants to admit.”
He groaned.
“Do not tell her that.”
“You both hide information to see whether people like you for the right
reasons.”
“That sounds terrible.”
“It is a little terrible.”
He nodded.
Then he told me everything.
The trust would not make us private-jet rich.
But it was substantial.
He also had investments and a future ownership stake in his father’s
company.
I told him about my student loans and retirement savings.
For the first time, our future finances existed in the same room as our
future marriage.
That was healthier than romance pretending money did not matter.
PART 16
A week later, Victoria called Mom.
Mom put the phone on speaker only after asking Victoria’s permission.
“I owe you a proper apology,” Victoria said.
Mom listened.
“I judged you based on your clothes. I disguised insults as
conversation. And when Ethan confronted me, I cared more about being
embarrassed than about what I had done.”
Mom glanced at me.
That was a real apology.
No “if.”
No “but.”
No explanation pretending to be an excuse.
“I accept,” Mom said.
Victoria hesitated.
“Can I ask something?”
“Yes.”
“Did I fail your test?”
Mom smiled.
“This wasn’t a college entrance exam.”
“You know what I mean.”
“You behaved badly.”
Victoria winced.
“But you also listened when people stopped protecting you from hearing
that.”
There was silence.
Then Mom added:
“That matters more to me than pretending good people never behave
badly.”
I remembered that sentence for years.
PART 17
The wedding planning changed after that dinner.
Not dramatically.
Victoria still liked expensive things.
Mom still thought spending thousands on decorative napkin rings was
evidence of temporary insanity.
They disagreed constantly.
But the disagreements became direct.
When Victoria suggested a luxury invitation suite, Mom said, “That is
absurd.”
Victoria replied, “You wore a twenty-eight-dollar dress to an engagement
dinner. Your judgment is compromised.”
Mom laughed.
They eventually became strange friends.
Not best friends.
Not sentimental movie mothers.
But women who respected each other enough to disagree honestly.
The flowers became Mom’s contribution.
She chose local peonies, roses, and greenery.
They were beautiful.
Victoria offered to pay the difference when the florist quote exceeded
Mom’s budget.
Mom accepted.
That mattered too.
Accepting help without shame was something Mom had never been good at.
Apparently, everyone at that table had something to learn about money.
PART 18
Ethan and I started premarital counseling.
Not because our relationship was failing.
Because the dinner exposed how easily family patterns can enter a
marriage unnoticed.
Ethan admitted he had spent his childhood managing Victoria’s moods.
He was skilled at redirection.
Jokes.
Subject changes.
Strategic exits.
Those skills kept peace.
They also made him slow to confront disrespect.
I had my own pattern.
I became embarrassed by Mom’s dress before anyone had said anything
cruel.
I had internalized some of the same class anxiety I disliked in
Victoria.
That realization was uncomfortable.
Why had I been ashamed?
Mom was clean.
Appropriate.
Kind.
The dress was merely old.
I had imagined the judgment before Victoria voiced it.
That meant part of the problem was already inside me.
I apologized to Mom.
She hugged me.
Then she said, “Good. Now stop acting like my wardrobe is a public
emergency.”
PART 19
Three months before the wedding, another test arrived.
This one was not planned.
Robert’s company hosted a charity gala.
Ethan and I attended.
Mom declined because she was volunteering at a food pantry fundraiser
the same night.
At the gala, one of Robert’s longtime business associates asked about my
family.
“What does your mother do?”
“She’s retired.”
“From?”
“Retail and office cleaning.”
His expression shifted.
Barely.
But I saw it.
Then he said, “Well, you’re certainly marrying up.”
Before I could answer, Ethan did.
“No.”
The man blinked.
Ethan continued.
“Claire is marrying me. She isn’t being promoted.”
The man laughed awkwardly.
“I didn’t mean anything.”
“I know. But that phrase means something whether you intend it or not.”
Ethan’s tone was calm.
No drama.
No waiting.
No subject change.
I looked at him and thought:
Mom would approve.
PART 20
She did.
When I told her, she smiled.
“Good.”
“That’s all?”
“What do you want, a certificate?”
“I thought you’d be more excited.”
“Claire, the goal was never to train your fiancé like a dog.”
I laughed.
“The goal was to know whether he could grow.”
Then Mom became serious.
“People reveal character in two ways.”
“What are they?”
“How they treat someone they think cannot benefit them.”
She paused.
“And what they do after they discover they behaved badly.”
That second part was the one I had almost missed.
If I judged Victoria only by the engagement dinner, I would have
understood something true about her.
But not everything true.
She had been cruel.
She was also capable of shame, apology, and change.
Ethan had been too passive.
He was also capable of recognizing it and behaving differently.
Character was not a frozen photograph.
It was a pattern.
PART 21
Our wedding arrived on a warm September afternoon.
Mom wore a deep blue dress.
New.
Elegant.
Perfectly fitted.
When Victoria saw her, she pressed a hand dramatically to her chest.
“Who are you, and what have you done with Margaret?”
Mom replied, “I decided not to emotionally traumatize you twice.”
They hugged.
Before the ceremony, Mom came into the bridal room.
She carried the old floral dress in a garment bag.
“What are you doing with that?”
“Relax. I’m not changing.”
She removed a small square of faded floral fabric.
I stared.
“You cut Aunt Lisa’s dress?”
“The hem.”
She handed me the fabric.
“I thought you could carry it.”
I held the little piece in my palm.
Something old.
Something that looked worthless if you did not know the story.
I tucked it inside my bouquet ribbon.
Then Mom kissed my forehead.
“Remember what it means.”
“I know.”
“Tell me.”
“Price isn’t value.”
She smiled.
“Good girl.”
PART 22
Then she added:
“And don’t test your husband every time you’re insecure.”
I laughed.
“That too.”
The ceremony was beautiful.
At the reception, Victoria gave a toast.
I was nervous.
She began by welcoming everyone.
Then she looked at Mom.
“Several months ago, I met Margaret while she was wearing a dress I
judged immediately.”
A few people laughed because the family already knew the story.
Victoria continued.
“I was wrong about the dress, wrong about Margaret, and wrong about what
good manners actually mean.”
Mom’s expression softened.
“Good manners,” Victoria said, “are not knowing which fork to use. They
are making sure the person beside you never feels small for using the
wrong one.”
That line stayed with me.
Then she raised her glass.
“To Claire and Ethan. May your home always be a place where nobody has
to prove they belong.”
Mom cried.
So did I.
PART 23
Marriage did not magically eliminate family differences.
Victoria still loved country clubs.
Mom still preferred diners.
Robert still tried to escape conflict.
Ethan still occasionally redirected when he should speak.
I still occasionally worried about being judged.
But now we noticed.
That was the change.
Two years after the wedding, Ethan and I bought our first house.
His parents offered us a large gift toward the down payment.
We discussed it privately before accepting.
Were there expectations?
Would they expect influence over the neighborhood?
Decorating?
Future resale?
Victoria looked offended when we asked.
Then she stopped herself.
“That is a fair question.”
The gift came with no conditions.
We accepted part of it and financed the rest ourselves.
Mom contributed a dining table she found at an estate sale for four
hundred dollars.
Victoria initially hated it.
Then she learned it was handcrafted walnut.
Suddenly she loved it.
Mom never let her forget that.
PART 24
When our daughter Sophie was born, the two grandmothers became even
stranger together.
Victoria bought expensive baby clothes.
Mom bought secondhand books.
Sophie spit up on both equally.
One afternoon, I found Mom showing Victoria how to remove a stain from a
designer baby blanket using dish soap.
Victoria said, “If you tell anyone I’m doing this, I’ll deny it.”
Mom replied, “I have photographs.”
I stood in the doorway laughing.
Then I noticed something.
Mom was wearing the old floral dress.
Not at a restaurant.
Not as a test.
At home, holding my daughter.
The hem was slightly shorter where she had cut the fabric for my wedding
bouquet.
I no longer saw faded material.
I saw Aunt Lisa.
My childhood.
My mother’s hands.
A restaurant table.
A lesson.
And a family that had nearly allowed assumptions to define it.
I walked over and hugged her.
“What was that for?” she asked.
“Nothing.”
She smiled.
“Those are usually the best hugs.”
PART 25
Years later, when Sophie was old enough to understand, she found a
wedding photograph showing the fabric tied inside my bouquet.
“What’s this?”
I told her the story.
Not as a story about Grandma Margaret tricking rich people.
Not as a story about Grandma Victoria being a villain.
I told it accurately.
Margaret wore an old dress because she wanted to see how people behaved
when status disappeared.
Victoria judged her.
Robert stayed too quiet.
Ethan redirected instead of confronting.
I felt ashamed of my own mother.
Then people told the truth.
Some apologized.
Some changed.
Everyone learned something.
Sophie listened carefully.
“So Great-Aunt Lisa’s dress was magic?”
“No.”
“It made everybody tell the truth.”
I smiled.
“Maybe a little.”
She asked where the dress was.
Mom still had it.
PART 26
On Mom’s seventieth birthday, we held dinner at our house.
Nothing extravagant.
Ethan cooked.
Victoria brought wine.
Robert brought a cake.
Sophie made a card.
Mom arrived wearing the floral dress.
The fabric was softer and more faded than ever.
Victoria pointed at her.
“Absolutely not.”
Mom laughed.
“What?”
“We are not doing this again.”
“There’s no test.”
“I don’t believe you.”
Mom sat down.
Victoria looked at the dress, then at her.
“You know, I actually like it now.”
Mom smiled.
“That’s because you know the story.”
And there it was.
The entire lesson in one sentence.
We often call something cheap because we do not know its history.
We call someone unsuccessful because we do not know what they survived.
We call someone unsophisticated because their knowledge is different
from ours.
We call silence weakness when it may be observation.
We call wealth character when it is merely money.
Context changes what we see.
PART 27
After dinner, Mom and I sat alone on the porch.
“Do you regret doing it?” I asked.
“The dress?”
“The test.”
She thought for a while.
“Yes and no.”
“That’s helpful.”
“I’m old. I’m allowed complicated answers.”
I waited.
“I regret putting you in the middle without warning.”
“Thank you.”
“I regret assuming one dinner could tell me everything about Ethan.”
I nodded.
“But I don’t regret paying attention.”
Neither did I.
She took my hand.
“I was scared, Claire.”
That surprised me.
“Of what?”
“That you would spend your life trying to earn their approval.”
I looked through the window.
Inside, Ethan was arguing with Victoria about whether cake belonged in
the refrigerator.
Mom continued.
“I spent my life making sure you never had to believe money determined
your worth. Then you fell in love with a family that had so much of it.”
“You didn’t trust me?”
“I trusted you.”
She squeezed my hand.
“I didn’t trust how powerful belonging can feel.”
PART 28
I understood.
Mom had spent her life outside rooms like the Whitmores’ dining room.
She knew how tempting it could be to shrink yourself once you were
finally invited inside.
That was what she was really testing.
Not wealth.
Not manners.
Not even Ethan alone.
She wanted to know whether my future marriage would require me to become
embarrassed by where I came from.
For a few minutes that first night, it had.
I had looked at Mom’s faded dress and wished she were different.
That was the part of the story I was least proud of.
But it became the part I needed most.
Because the warning was not only:
Watch how rich people treat poor people.
It was:
Watch who you become when you want rich people to accept you.
That lesson followed me into every room afterward.
Boardrooms.
Fundraisers.
School events.
Country clubs.
Restaurants.
Whenever I felt myself adjusting my mother’s story to make it sound more
impressive, I stopped.
She had worked retail.
She had cleaned offices.
She had raised me.
Nothing about that needed polishing.
PART 29
Ethan learned something similar.
For years, he thought being a good son meant preventing conflict with
Victoria.
After our engagement dinner, he learned peace and respect were not the
same thing.
Sometimes peace required speaking.
Sometimes loyalty required disagreement.
Sometimes protecting a parent from embarrassment only protected the
behavior causing it.
His relationship with Victoria actually improved.
She trusted him more once he stopped managing her.
She still became defensive sometimes.
But now she recovered faster.
Once, years later, she made a dismissive comment about a waiter’s
accent.
Ethan said, “Mom.”
One word.
Victoria stopped.
Then she called the waiter back and apologized.
No family summit.
No drama.
No dessert crisis.
Just correction.
That was growth.
Not perfection.
Growth.
PART 30
Mom kept Aunt Lisa’s dress until the fabric finally became too fragile
to wear.
Then she did something I never expected.
She cut it apart.
From the usable fabric, she made four small cloth covers.
One for a photo album.
One for Sophie’s keepsake box.
One for me.
And one for Victoria.
When Victoria opened hers, she cried.
“I was horrible about this dress.”
Mom shrugged.
“You improved.”
“That’s not forgiveness.”
“It’s enough for a box.”
Victoria laughed through tears.
Inside her box, Mom had placed a handwritten note:
Never confuse what something costs with what it is worth.
Victoria kept it on her dressing table.
Years later, after Mom died, that little box was one of the first things
Victoria brought to me.
“I think this belongs with you.”
I shook my head.
“She made it for you.”
Victoria held it tighter.
Then she nodded.
PART 31
Mom’s funeral was not fancy.
That was intentional.
We held it in the small church she attended for decades.
The flowers were local.
The food afterward came from the neighborhood diner she loved.
Victoria arrived early.
She wore a simple navy dress.
No jewelry except her wedding ring.
She stood beside me while people came through the receiving line.
Former coworkers.
Neighbors.
Women Mom had helped with childcare.
A man whose grocery bill she once paid.
A former office supervisor.
People from every part of her life.
Victoria whispered, “I thought I understood wealth.”
I looked at the crowded church.
“So did I.”
Ethan held my hand.
Sophie carried the keepsake box covered in Aunt Lisa’s floral fabric.
Mom had once worn that dress to learn how my future family would treat
someone they believed was beneath them.
At her funeral, there was no one in the room who believed she had ever
been beneath anyone.
PART 32
Years have passed since that engagement dinner.
If you ask Ethan what he remembers most, he says the chocolate mousse
arriving during the argument.
If you ask Victoria, she says the moment Mom admitted the dress was a
test.
If you ask Robert, he says the sandwiches at Mom’s seventieth birthday
were better than the engagement dinner.
He is wrong.
But if you ask me, I remember the restroom mirror.
Mom standing beside me in that faded floral dress.
Me admitting I was embarrassed.
And her saying:
“I wanted to see how they would treat someone they believed was beneath
them.”
At the time, I thought she was testing wealthy people.
She wasn’t.
Not entirely.
She was testing whether Ethan would choose comfort over courage.
Whether his parents would confuse money with worth.
Whether I would become ashamed of the woman who had sacrificed
everything to raise me.
And whether, once the truth was visible, any of us could change.
That last test was the one that mattered most.
PART 33
The engagement dinner did not prove that Ethan was perfect.
It proved he was capable of recognizing when silence became complicity.
It did not prove Victoria was irredeemably cruel.
It exposed a fear she had transformed into snobbery—and gave her the
chance to confront it.
It did not prove Mom was always right.
She later admitted that testing people without their knowledge could
itself be unfair.
And it certainly did not make me innocent.
Before Victoria said a word, I had already looked at my mother’s dress
and decided it did not belong in the room.
That realization changed me.
The dress was old.
The fabric was faded.
The style was outdated.
But none of those facts said anything about the woman wearing it.
Mom had raised a child alone.
Worked two jobs.
Saved carefully.
Loved fiercely.
And walked into a room full of people with more money than she had
without needing their approval.
I had mistaken polish for dignity.
Mom knew dignity had nothing to do with polish.
PART 34
That is why, when Sophie became engaged many years later, I told her the
story again.
Her fiancé came from a completely ordinary family.
No country club.
No trust fund.
No dramatic class divide.
Still, the lesson applied.
“Watch how people treat someone who cannot do anything for them,” I told
her.
Sophie smiled.
“Grandma Margaret.”
“Yes.”
“And don’t secretly test everyone.”
“Also Grandma Margaret.”
She laughed.
Then I gave her the small floral-covered keepsake box.
Inside was the piece of Aunt Lisa’s dress that had been tied to my
wedding bouquet.
Sophie touched the faded fabric.
“It’s still ugly.”
I gasped.
“Your grandmother would haunt you.”
“She’d agree.”
She probably would have.
Then Sophie closed the box.
“I know what it means.”
“What?”
“That value has a story.”
I smiled.
“Exactly.”
PART 35
My mother wore the most worn-out dress she owned to my engagement
dinner.
For the first hour, I wished she hadn’t.
For the rest of my life, I was grateful she did.
Not because humiliating people is a good way to test character.
It isn’t.
Not because wealthy people are automatically shallow.
They aren’t.
And not because an old dress makes someone morally superior.
It doesn’t.
I was grateful because that evening forced all of us to see patterns we
had learned to ignore.
Victoria saw what fear of being judged had turned her into.
Robert saw how often he protected peace instead of people.
Ethan saw the difference between redirecting cruelty and confronting it.
Mom saw that even a well-intended test could become manipulation.
And I saw how quickly I could become ashamed of the very history that
made me who I was.
The dinner was supposed to celebrate an engagement.
Instead, it taught us what marriage would require.
Not matching backgrounds.
Not matching bank accounts.
Courage.
Honesty.
Boundaries.
And the willingness to notice when someone at the table is being made
smaller.
That was what Mom had been watching for before dessert.
And in the end, it was worth far more than anything anyone at that table
could have bought.







